Burnout or Depression? The Distinctions That Actually Matter
Quick Answer: The clearest practical distinctions are context and recovery: burnout is tied to a specific domain, usually work, and symptoms typically ease meaningfully when you’re genuinely away from it - while depression tends to be pervasive across all areas of life and doesn’t lift with a break. Burnout centres on exhaustion and cynicism about a role; depression more commonly includes persistent low mood, loss of pleasure in everything, and feelings of worthlessness. They overlap substantially and can occur together, which is why a professional assessment matters.
The two are frequently confused, including by the people experiencing them, and it matters because the responses are different. Restructuring your job doesn’t treat depression. Treating depression doesn’t fix an unsustainable workload.
This is general information, not medical advice or diagnosis. If you’re struggling, a GP or mental health professional can assess your situation properly. If you’re having thoughts of harming yourself, contact your local emergency or crisis service now - in the UK, Samaritans is 116 123, free, any time.


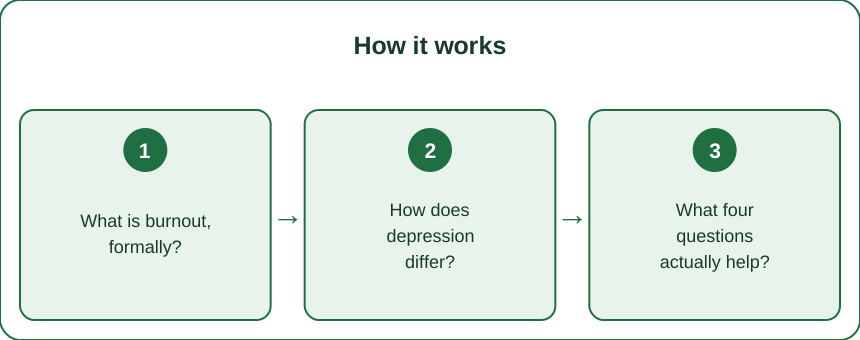
What is burnout, formally?
It has a specific definition, and the specificity is useful.
The World Health Organization classifies burnout in ICD-11 as an occupational phenomenon - explicitly not a medical condition - resulting from chronic workplace stress that hasn’t been successfully managed. It’s characterised by three dimensions:
- Exhaustion - energy depletion that rest doesn’t resolve
- Mental distance from the job, or feelings of negativism and cynicism about it
- Reduced professional efficacy - a sense of being less capable at the work
Two things in that definition do a lot of work.
First, it’s occupational. It refers specifically to phenomena in the work context and isn’t meant to describe experiences in other areas of life - though in practice the same pattern clearly occurs in caregiving, parenting, and other sustained demanding roles.
Second, it’s not classified as a medical condition. It’s a description of an occupational phenomenon, which has a practical consequence: there’s no diagnosis and no treatment protocol for burnout in the way there is for depression. What there is instead is changing the conditions producing it.
The cynicism dimension is the most distinctive feature. Exhaustion is common to many things. The specific development of detachment, cynicism, or negativity about a role you previously cared about is the marker most characteristic of burnout, and it’s often the first thing colleagues notice.
How does depression differ?
Depression is a clinical condition with diagnostic criteria, and several features distinguish it.
Core features typically include persistent low mood and loss of interest or pleasure, present most of the day nearly every day for at least two weeks, along with things like changes in sleep and appetite, fatigue, difficulty concentrating, feelings of worthlessness or excessive guilt, and in some cases thoughts of death or self-harm.
The features that most help distinguish it from burnout:
Pervasiveness. Depression generally affects everything - work, relationships, hobbies, things you’d normally enjoy. Burnout is more commonly domain-specific: exhausted and cynical about work, but still able to enjoy a weekend with friends.
Worthlessness versus ineffectiveness. Burnout typically involves feeling ineffective at the job. Depression more often involves feelings of worthlessness as a person, which is a broader and more corrosive thing.
Anhedonia. The loss of pleasure in things you previously enjoyed, across the board, is a core depressive feature. Someone with burnout usually still enjoys things away from the source.
Response to removal. This is the most practically useful distinction available. Burnout symptoms typically improve meaningfully during a genuine, extended break from the source. Depression usually doesn’t lift with a holiday.
The important complication: they overlap substantially, they can occur together, and prolonged burnout is associated with an increased risk of developing depression. Distinguishing them is a job for a professional, not a checklist - the value of understanding the difference is in knowing what to ask about, not in self-diagnosing.
What four questions actually help?
Not diagnostic - these are for figuring out what to bring to a conversation with a professional.
1. Is it everywhere, or is it one area?
Ask yourself specifically: when you’re doing something you used to enjoy, away from work entirely, is it still flat? Domain-specific points toward burnout; pervasive points toward depression.
2. What happens on a real break?
Not a long weekend - a genuine two weeks away, without email. Burnout typically improves noticeably. Depression typically doesn’t, and can even feel worse without the structure work provided.
The caveat that matters: severe burnout may not resolve in two weeks either, and returning to unchanged conditions brings it straight back. The signal is whether there’s meaningful improvement, not whether it fully resolves.
3. How do you feel about yourself, versus about the role?
‘I’m useless at this job and I’ve stopped caring about it’ points toward burnout. ‘I’m a failure as a person and nothing I do matters’ points toward depression, and warrants a professional conversation soon.
4. Is there a plausible cause proportionate to it?
Burnout usually has an identifiable history - a sustained period of excessive demand, insufficient control, unfairness, or values conflict. Depression can occur without any proportionate external cause, and the absence of an obvious reason is itself informative.
Two things that override all four: thoughts of death or self-harm, and symptoms severe enough that you can’t function day to day. Either means seeing a doctor promptly, regardless of which label seems to fit.

Myth vs Fact: Burnout and Depression
Myth: Burnout just means you’re tired and need a holiday. Fact: Burnout involves exhaustion, cynicism, and reduced efficacy developing over months, and it’s associated with real health consequences. A holiday helps temporarily; returning to the same conditions brings it back within weeks, which is why ‘take a break’ as the whole solution so consistently fails.
Myth: Depression always has an obvious cause. Fact: It often doesn’t. Depression can develop without a proportionate external trigger, and the search for a reason can delay people from seeking help. The absence of an explanation is not evidence against it.
Myth: If you can still function at work, it isn’t depression. Fact: Many people with depression continue working, sometimes to a high standard, at significant internal cost. Continuing to function is not evidence of being fine, and it’s a common reason people delay getting help for years.
Myth: Burnout is a personal failure of resilience. Fact: Burnout is understood as arising from the conditions of work - workload, control, reward, community, fairness, and values - rather than from individual weakness. Framing it as a resilience deficit places responsibility on the person and away from the conditions that produced it, which is both inaccurate and unhelpful.
Myth: You can’t have both. Fact: You can, and prolonged burnout is associated with increased risk of depression. This is a substantial reason not to self-diagnose and wait it out.
What actually helps, for each?
Different problems, different responses - and there’s overlap in the basics.
For burnout, the effective interventions target conditions:
- Reduce the demand, genuinely. Fewer hours, fewer responsibilities, or a different role. Interventions that only teach individual coping while leaving workload unchanged have limited effect - the research on this is fairly consistent and fairly discouraging for the self-care-only approach.
- Increase control. Autonomy over how and when you work is one of the strongest protective factors.
- Address the specific driver. Workload, lack of control, insufficient reward, breakdown of community, unfairness, and values conflict are the recognised domains. Identifying which applies to you is what makes the change targeted rather than generic.
- Recovery time that’s actually recovery - genuinely disconnected, not available on email
- Reconnect with why the work mattered, if it did. The cynicism dimension often responds to this.
For depression, evidence-based treatment:
- Talking therapies, with CBT among the best-supported
- Medication, where appropriate, discussed with a doctor
- Behavioural activation - gradually re-engaging with activity, one of the more effective components
- Exercise, which has reasonable evidence for mild to moderate depression
- Regular sleep and reduced alcohol
What helps both: sleep, movement, sunlight, social contact, and reducing alcohol. These are worth doing regardless of which applies - and they are not a substitute for assessment if things are significant.
The single most useful step, for either: talk to a GP. You don’t need to know which it is before you go - working that out is part of what the appointment is for, and going with ‘I’ve been exhausted and flat for three months and I don’t know why’ is a completely reasonable way to start.
FAQ: Burnout and Depression, Answered
Can burnout turn into depression?
Prolonged burnout is associated with increased risk of depression, and they share features and often co-occur. It’s a strong argument for addressing burnout early rather than waiting to see whether it resolves on its own.
How long does recovery from burnout take?
Highly variable - weeks for mild cases where conditions change quickly, and many months for severe cases. The most consistent finding is that recovery is much slower if the underlying conditions don’t change, which is why time off alone so often doesn’t work.
Should I quit my job?
Sometimes the answer is yes, and it’s rarely a decision to make in the middle of the worst of it. Explore reduced hours, changed responsibilities, a different team, or sick leave first. Making a major life decision while severely burnt out is a well-recognised way to make a poorly-judged one.
Is there a test I can take?
There are validated research instruments such as the Maslach Burnout Inventory, and screening tools for depression like the PHQ-9. Online versions are indicative rather than diagnostic - useful as a starting point for a conversation with a professional, not as a conclusion.
What if my workplace caused it and won’t change?
That’s a genuinely difficult situation and a common one. Occupational health, HR, or your union may have options, and in some jurisdictions there are legal protections around work-related stress. In the meantime, protecting recovery time and limiting availability outside hours are the levers you control.
TL;DR:
- Burnout is an occupational phenomenon defined by exhaustion, cynicism about the role, and reduced efficacy
- Depression is a clinical condition that’s typically pervasive rather than domain-specific
- Four useful questions: is it everywhere, does a real break help, is it about you or the role, and is there a proportionate cause
- Burnout responds to changed conditions; individual coping strategies alone have limited effect
- Depression responds to therapy, sometimes medication, behavioural activation, and exercise
- They overlap and can co-occur - and you don’t need to know which it is before seeing a GP
The distinction matters because the responses are different. But the first step is the same either way, and it’s a conversation with someone who can actually assess it.
Keep Reading
This article is for general informational purposes only and is not medical advice. Always consult a qualified health professional for guidance specific to you.